Tag: Healthcare Costs

  • Trump Cuts May Widen Racial Health Gaps

    Public health experts are sounding the alarm: federal funding cuts, particularly those targeting diversity, equity, and inclusion (DEI) initiatives, could significantly widen the gap in racial health disparities across the United States. As states, universities, and nonprofits grapple with the loss of federal dollars, programs designed to address critical healthcare access and outcomes for minority communities are being rolled back.

    The Impact of Federal Restructuring

    The Trump administration’s federal restructuring and crackdown on DEI programs have led to the termination of hundreds of grants. These grants were crucial for state, local, and territorial health departments, as well as nonprofits and universities, in their efforts to promote health equity in rural areas, low-income communities, and communities of color. The shake-up has forced some organizations to pause vital programs or scramble for alternative funding from private foundations.

    These disparities were starkly highlighted during the COVID-19 pandemic, which disproportionately affected Black, Hispanic, and Indigenous populations. The subsequent racial reckoning in 2020 spurred various initiatives aimed at addressing these inequities, from targeted vaccine drives to correcting biased diagnostic tools. However, the current rollback of these programs threatens to undo much of that progress.

    A Deepening Divide in Healthcare Access

    Communities of color have historically faced significant barriers to healthcare, including less access to care, higher exposure to environmental pollutants, and a greater prevalence of chronic illnesses like diabetes and certain cancers. These existing vulnerabilities mean that any reduction in targeted support can have severe consequences, leading to more late-stage diagnoses and poorer health outcomes.

    Dr. Georges Benjamin, executive director of the American Public Health Association, expressed deep concern, stating, “My concern about what the administration is doing is that they are, in effect, making these disparities worse.” He emphasized that DEI is not merely a political agenda but an “American agenda,” akin to the principle that “rising tides lift all boats.” Cutting these resources disproportionately harms those already most impacted.

    Billions in Grants Canceled

    The administration has canceled billions of dollars in grants from major federal agencies, including the National Institutes of Health (NIH), the Centers for Disease Control and Prevention (CDC), the Environmental Protection Agency (EPA), and the Department of Health and Human Services (HHS). Many of these grants funded community-specific solutions and pandemic-preparedness efforts.

    At least three dozen state, local, and territorial health departments have seen their pandemic-era grants for health equity terminated. While originally focused on COVID-19, this funding was repurposed for broader public health initiatives like disease tracking, data reporting, and community partnerships addressing social determinants of health. The Department of Health and Human Services cited the end of the pandemic emergency in 2023 as the reason for these cancellations.

    Impact on Research and State Programs

    The NIH alone saw over 5,400 research grants terminated, though some were later reinstated. Canceled research included critical studies on illnesses like HIV and AIDS, which disproportionately affect Black, Hispanic, gay, and transgender populations. Furthermore, federal offices dedicated to fighting health disparities, such as the Offices of Minority Health within CMS and HHS, have been significantly reduced.

    At the state level, this has led to difficult decisions. The Arkansas Department of Health, for instance, recently closed its minority health-focused office, citing reliance on federal grant funding. While Maryland’s Department of Health stated its minority health office is state-funded and unaffected, the overall trend points to a significant reduction in resources.

    Medicaid Cuts and Data Collection Concerns

    Adding to the concern are changes to Medicaid included in a recent tax and spending law, projected to cut federal Medicaid spending by an estimated $911 billion over a decade. New work requirements are expected to push many individuals off the rolls, disproportionately affecting Black and Hispanic populations who are heavily represented in Medicaid enrollment. Experts like Dr. Versha Pleasant, an OB-GYN, highlight that Black women already face a nearly 40% higher risk of death from breast cancer than white women, a disparity that these changes are likely to magnify.

    Furthermore, federal officials are reportedly informing health agencies that race and ethnicity data are no longer required for reporting. While some counties, like Santa Clara in California, are committed to continuing data collection to understand community needs, others may lack the resources. This loss of granular data could hinder efforts to track and address health disparities effectively.

    A Formula for Problems

    The combination of declining capacity at health departments and increasing community needs creates a challenging environment. “You’ve got declining capacity, and increasing need — which is a formula for problems,” stated Richard Frank, director of the Brookings Institution Center on Health Policy. He and other experts worry that without adequate federal support, vital programs serving vulnerable populations will be scaled back, leading to a widening of the racial health divide.

    What are your thoughts on these federal funding cuts and their potential impact on racial health disparities? Share your concerns and ideas in the comments below.


  • New Law May Limit Hospital Care for Low-Income Patients

    A new federal law, the ‘One Big Beautiful Bill Act,’ is set to alter the landscape of healthcare for low-income Americans. Starting in 2028, this legislation will cap the supplemental payments that states can make to hospitals treating Medicaid patients. Critics warn this change could disproportionately harm rural hospitals and limit access to care for vulnerable populations.

    Understanding the Medicaid Reimbursement System

    Medicaid, the joint federal and state health insurance program for low-income individuals, reimburses healthcare providers. However, these reimbursements often don’t cover the full cost of care, creating financial strain for providers, especially those serving a large number of Medicaid patients. To help offset these losses, many states have utilized ‘state-directed payments,’ allowing Medicaid managed care organizations to pay providers more, sometimes aligning closer to commercial insurance rates.

    These supplemental payments have grown substantially, projected to add over $110 billion annually to Medicaid spending. This increase caught the attention of conservatives, leading to the new law that caps these payments. The goal is to reduce federal spending on Medicaid, but the consequences for healthcare providers are a major concern.

    Impact on Hospitals and Patients

    The ‘One Big Beautiful Bill Act’ mandates that state Medicaid programs reduce reimbursement rates annually until they reach either 100% or 110% of Medicare rates. According to the Congressional Budget Office, this could reduce Medicaid spending by $149 billion over the next decade. Health policy research groups estimate that Medicaid payments to hospitals could drop by at least 20% in many states.

    This reduction is particularly alarming for rural hospitals, which often have a higher proportion of Medicaid patients and fewer resources to absorb financial losses. Alexa McKinley Abel of the National Rural Health Association expressed worries about ‘service line closures,’ noting that OB-GYN and chemotherapy services are already being cut in some areas. Hospitals argue that without these supplemental payments, Medicaid only covers about two-thirds of the actual cost of care.

    Arguments for and Against the Law

    Supporters of the law, like the conservative think tank Paragon Health Institute, argue that the extra payments create ‘windfall profits’ and inflate federal spending, contributing to inflation and higher interest rates. They believe these programs favor special interests over the truly needy.

    However, hospital leaders strongly dispute this. Cindy Samuelson of the Kansas Hospital Association highlighted that in rural states like Kansas, where many hospitals are already operating at a loss, these additional payments are a lifeline. She noted that as commercial payers reduce their rates, hospitals become increasingly reliant on Medicaid reimbursements to stay afloat. The reduction in payments could force rural hospitals to trim services further, impacting the entire community’s access to healthcare.

    Seeking Sustainable Solutions

    Hospitals are exploring various avenues to cope with the impending changes. Some, like Hutchinson Regional Health System in Kansas, are relying more heavily on philanthropy and managing workforce expenses by not filling open positions. Others are looking to funds like the Rural Health Transformation Program, a $50 billion initiative added to the bill, which aims to support rural hospitals. States like Kansas and Mississippi are applying for these funds, hoping for at least $500 million each over the next five years.

    Richard Roberson of the Mississippi Hospital Association emphasized the need for ‘sustainable solutions, not one-time fixes,’ expressing concern that without the enhanced supplemental payments, rural hospitals could face closure threats similar to those seen in 2022. The effectiveness of the new rural health care fund and how states allocate these resources will be critical in determining the future of healthcare access in underserved communities.

    What are your thoughts on the new law capping Medicaid payments? How do you think it will affect healthcare access in your community? Share your views in the comments below!

  • Virginia Healthcare Policies Under Scrutiny

    The BlackDoctor Policy Hub launched its new “Lunch & Learn” series with a vital conversation focusing on three complex yet impactful healthcare policies: the 340B Program, Pharmacy Benefit Managers (PBMs), and Most Favored Nation (MFN) policies. Moderated by BDO’s Executive Editor Jade Curtis, the session featured industry and physician experts discussing how these policies affect healthcare costs, drug access, and communities, particularly in Virginia.

    Understanding the 340B Program and MFN Policies

    John Newby, CEO of Virginia BIO, provided context on the 340B program, established in 1992 to provide deep drug discounts to safety-net hospitals. The program’s intent is to allow these hospitals to reinvest savings into care for underserved patients, leading to lower drug prices and expanded services when implemented correctly. However, Newby cautioned that misuse and a lack of oversight often prevent patients from realizing these benefits.

    He also addressed MFN policies, which link U.S. drug prices to those in other developed nations. While seemingly fair, Newby warned that such policies could stifle innovation, reduce access to new therapies, and ultimately harm patients if investors cannot see a return on investment. “If investors can’t see a return, innovation suffers—and patients lose,” he explained.

    The Role of PBMs and Program Misuse

    Newby described PBMs as “middlemen” who profit from higher list prices, creating incentives to favor more expensive drugs over cheaper alternatives. Dr. Harry Gewanter, a pediatric rheumatologist and President of the Virginia Society of Rheumatology, highlighted data showing that the 340B program in Virginia has deviated from its original purpose. Shockingly, 67% of Virginia’s 340B hospitals provide below-average charity care while generating profits three times greater than their community reinvestment.

    Dr. Gewanter stated, “The program has been hijacked,” pointing out that contract pharmacies, including major chains like Walgreens and CVS, are often located far from the underserved communities the 340B program was intended to serve. Both speakers emphasized the critical need for transparency and accountability to rebuild trust in these systems.

    Calls for Reform and Community Action

    The discussion underscored that patients rarely know when their prescriptions are linked to 340B discounts, and there’s no robust system ensuring savings reach vulnerable populations. Dr. Gewanter advocated for reforms including clear eligibility standards, stronger oversight, and meaningful penalties for program abuse, stating, “We need standards, enforcement with teeth, and real consequences.”

    The Protect 340B Act, a bipartisan bill aimed at preventing discrimination against 340B providers by insurers and PBMs, was also discussed. While seen as a positive step, both speakers agreed that further legislative action is needed to truly protect patients and preserve safety nets.

    In closing, the importance of community engagement was stressed. Newby encouraged individuals to stay informed and involved, reminding them, “You are your best advocate. Don’t sit back and be passive.” Dr. Gewanter echoed this sentiment, urging, “If you want things to change, you have to be involved. Ask questions. Push your legislators. Demand accountability.”

    This inaugural Lunch and Learn session highlighted that systemic healthcare reform requires persistence, policy changes, and active community involvement. By illuminating complex policies like 340B, PBMs, and MFN, the BlackDoctor Policy Hub aims to translate knowledge into action, empowering communities to demand meaningful change.

    What are your thoughts on the current state of healthcare policies like 340B? How can we better advocate for transparency and accountability? Share your views in the comments below!

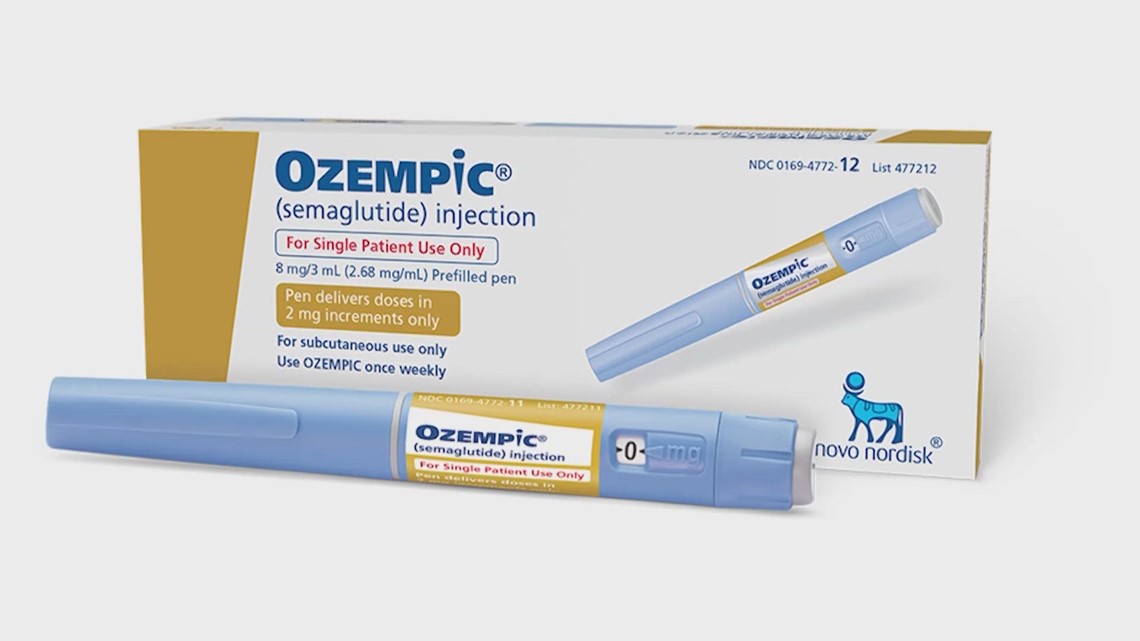
  • Ozempic Price Slashed for Uninsured Patients

    Big news for anyone struggling to afford popular medications! Novo Nordisk, the company behind Ozempic, has announced a major price drop for its widely used diabetes and weight loss drug. For patients paying out-of-pocket, Ozempic is now available for $499 a month, a substantial decrease from its previous price of nearly $1,000.

    Making Ozempic More Accessible

    This price reduction is being offered through NovoCare Pharmacy, a direct-to-consumer service. By cutting out the middleman of insurance companies, Novo Nordisk aims to make the medication more accessible to those without insurance coverage. This move comes amid increasing pressure from lawmakers, including former President Trump, who have highlighted the significant price disparities for medications in the U.S. compared to other countries.

    Ozempic, along with other GLP-1 drugs like Wegovy, has been a focal point in discussions about healthcare costs due to its dual use for diabetes management and weight loss. This price adjustment could be a game-changer for many Americans facing high medical bills.

    A Wider Trend in Drug Pricing?

    This isn’t the first time Novo Nordisk has offered its GLP-1 drugs at this lower price point; Wegovy was also made available for $499 a month through their pharmacy earlier this year. Competitor Eli Lilly has also responded by lowering the price of its GLP-1 drug, Zepbound, for self-pay patients. This suggests a potential shift in how pharmaceutical companies are approaching pricing for self-paying customers.

    While this price cut is welcome news for many, it also raises an important question: if drug companies can afford to offer these medications at such a significantly lower price now, why were patients paying double for so long? It’s a complex issue with many layers, but for now, the accessibility of Ozempic has certainly improved for a significant portion of the population.

    What are your thoughts on this Ozempic price drop? Do you think other drug companies will follow suit? Share your opinions in the comments below!